GI Endoscopy · 2 min read
Ileocecal Diffuse Large B-Cell Lymphoma Diagnosed by Colonoscopic Biopsy
A 63-year-old man with an exophytic ileocecal-valve mass. Targeted biopsies showed DLBCL. Six cycles of R-CHOP, then complete metabolic response.
Experienced teaching points
Clinical Pearls
- An exophytic, lobulated ileocecal mass should prompt lymphoma in the differential. Do not treat it automatically as adenocarcinoma.
- Adequate targeted biopsies can establish the diagnosis before definitive treatment planning.
- This lesion arose from the ileocecal valve. The remaining examined colonic mucosa was unremarkable.
- Once the report is DLBCL, refer to Hematology. This patient received six cycles of R-CHOP. Follow-up PET/CT was consistent with a complete metabolic response.
Get cases like this Saturday mornings. Free, no spam.
| Patient: | 63-year-old man with 6 months of abdominal pain, 25-lb weight loss, and nocturnal fever |
| Indication: | Ileocecal mass on CT, concerning for malignancy. Lymphoma stayed on the differential |
| Final diagnosis: | Ileocecal-valve diffuse large B-cell lymphoma (DLBCL), germinal-center phenotype, without a double-expressor phenotype |
Clinical History
A 63-year-old man with no relevant comorbidities presented with 6 months of generalized abdominal pain, a 25-lb unintentional weight loss, and nocturnal fever. Labs showed microcytic hypochromic anemia with hemoglobin of 10.4 g/dL, low serum iron, and elevated lactate dehydrogenase of 490 U/L. Contrast-enhanced abdominal CT showed an infiltrative mass involving the cecum and right colon, with extrinsic ureteral compression and right hydronephrosis. The appearance was concerning for an ileocecal malignancy. Lymphoma stayed on the differential.
Endoscopic Findings
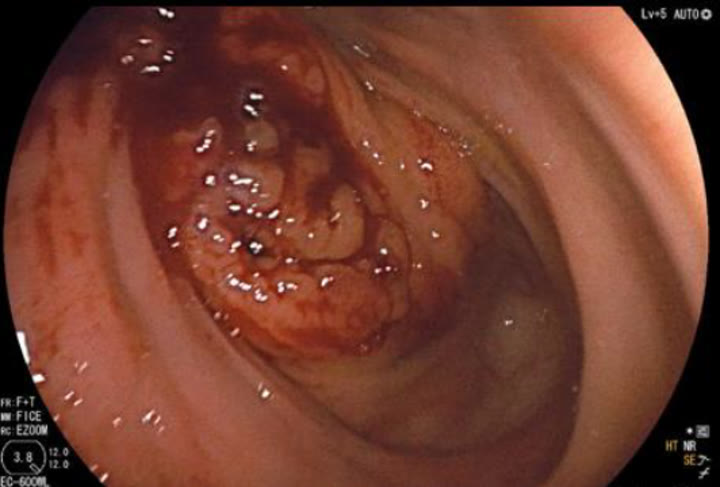
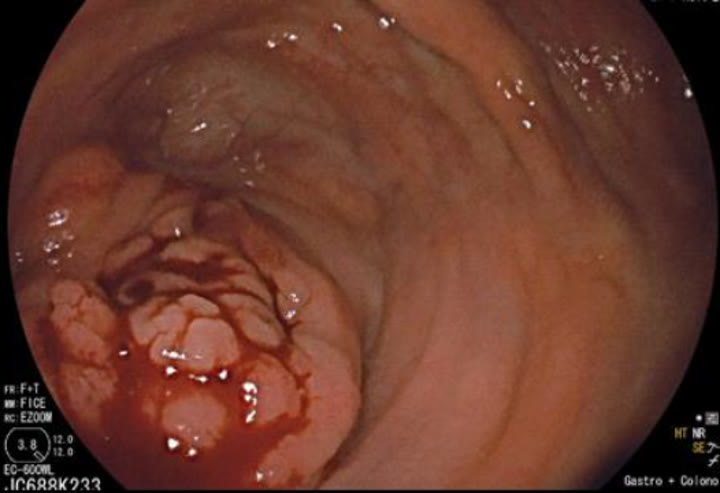
- A large exophytic, endoluminal lesion arising from the ileocecal valve.
- An irregular, lobulated surface with marked distortion of the local anatomy.
- The remaining examined colonic mucosa was unremarkable.
Pathology
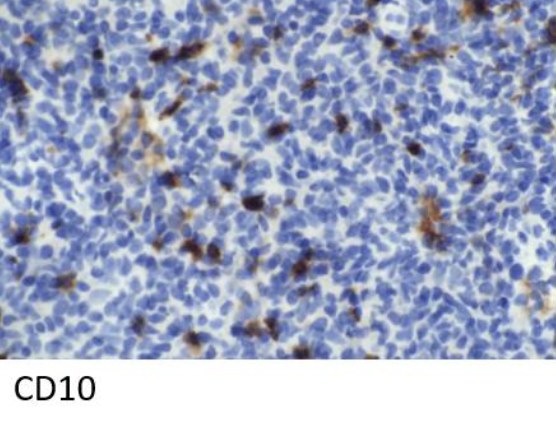
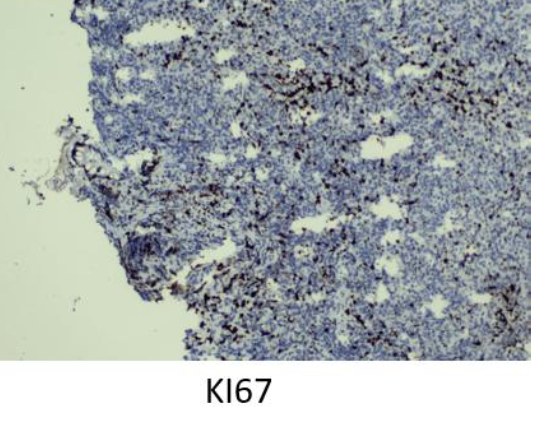
Histopathology showed infiltration of the lamina propria by medium-to-large atypical lymphoid cells. Immunohistochemistry was positive for CD20 and supported a germinal-center phenotype. CD10 expression and Ki-67 nuclear labeling were also demonstrated. The findings established DLBCL without a double-expressor phenotype.
Staging
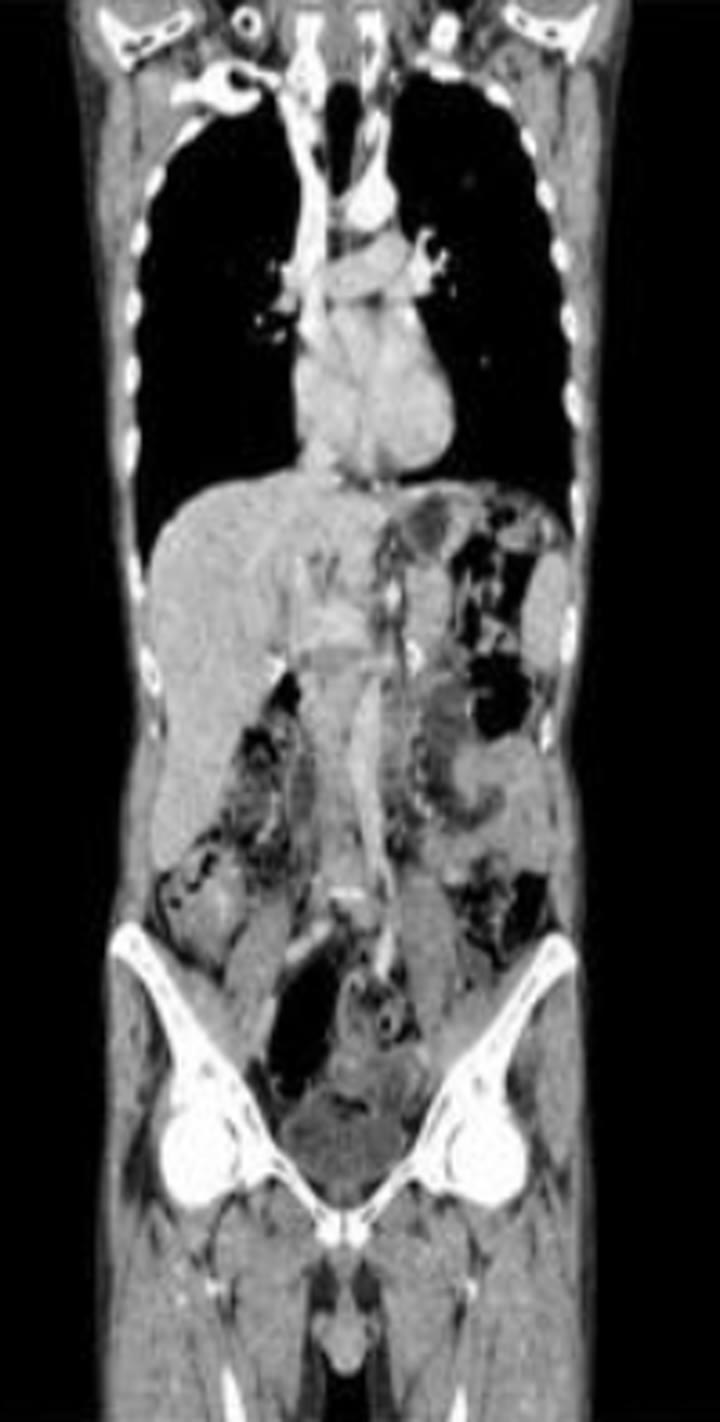
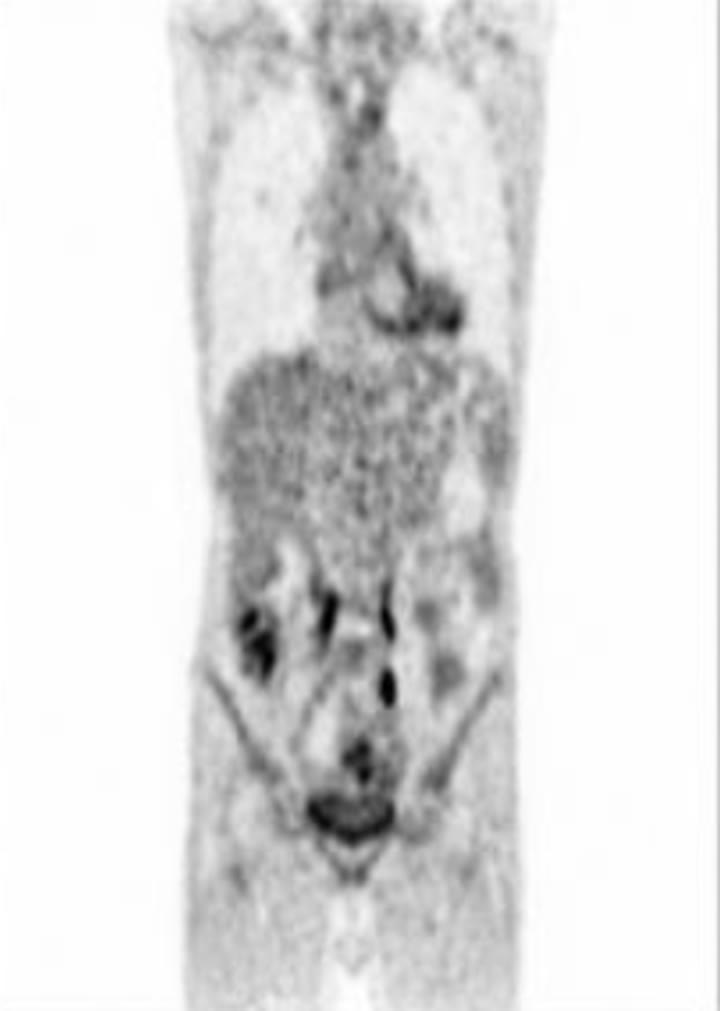
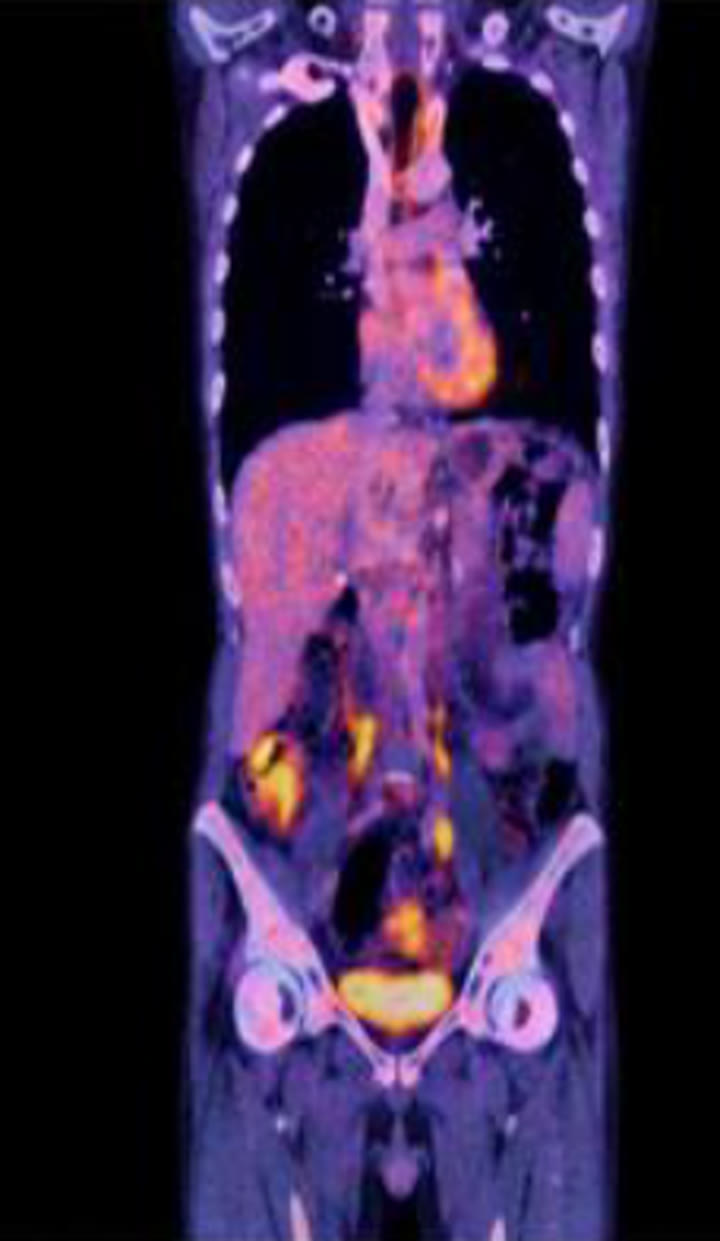
Baseline PET/CT demonstrated metabolically active thickening of the cecal/ileocecal region.
Endoscopic Technique
Colonoscopy with multiple targeted biopsies of the ileocecal-valve lesion.
Discussion
Colorectal lymphoma may involve the ileocecal region and can present with a polypoid or mass-like morphology. A lobulated, exophytic ileocecal mass can look like adenocarcinoma until histology names it.
Panels A and B are the colonoscopic lesion: exophytic, endoluminal, arising from the ileocecal valve, irregular and lobulated, with local anatomic distortion. The rest of the examined colon was unremarkable. Baseline PET/CT then showed metabolically active cecal/ileocecal wall thickening.
Careful inspection and adequate targeted biopsies can establish DLBCL before definitive treatment planning. This patient was referred to Hematology and received six cycles of R-CHOP. Follow-up PET/CT showed disappearance of the previously hypermetabolic intestinal lesions, consistent with a complete metabolic response.
References
- Yachida T, Matsuda T, Sakamoto T, et al. Endoscopic features of colorectal lymphoma according to histological type. JGH Open. 2022;6(4):257-262.
- Vetro C, Romano A, Amico I, et al. Endoscopic features of gastro-intestinal lymphomas: from diagnosis to follow-up. World J Gastroenterol. 2014;20(36):12993-13005.
- Lightner AL, Shannon E, Gibbons MM, Russell MM. Primary gastrointestinal non-Hodgkin's lymphoma of the small and large intestines: a systematic review. J Gastrointest Surg. 2016;20(4):827-839.
For your teaching file
Save this article as a PDF
Drop your email and we'll open a print-ready version you can save as a PDF. You'll also start getting our GI endoscopy newsletter Saturday mornings.